

Physical Therapy revenue depends on certified plans, supported minutes, and measurable progress.
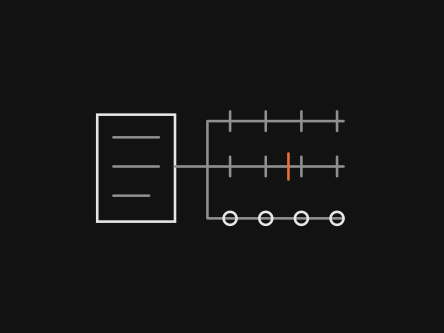
Physical therapy spans independent practices, hospital outpatient departments, physician-owned clinics, and rehabilitation sites. Revenue depends on referrals, authorized visits, and certified plans of care. Treatment records must support skilled need, functional goals, and direct minutes. Coding must then translate timed services, PTA participation, and modifiers into defensible claims.
7 of top 20
U.S. health systems served
32M+
Coding charts processed annually
28M+
A/R claims managed annually
Therapy minutes create revenue only when the record proves skilled progression.
Repeated visits magnify small access, documentation, and coding defects. An expired authorization can affect an entire treatment episode. Missing certification can weaken otherwise appropriate care. Incorrect unit allocation creates payment and audit risk. Therapy specialists, RevAmp intelligence, and accountable governance connect each visit to the plan, payer rule, and financial result.
Keep authorized visits aligned with the treatment episode
Convert direct treatment minutes into supported units
Prove functional progress before continued-care review
Support built around authorized visits, certified plans, timed units, and therapy modifiers.
Therapy providers need revenue cycle support that follows the complete episode. Front-office workflows must confirm benefits, referrals, authorizations, and visit limits. Mid-office controls must align plans of care, progress notes, direct minutes, units, and modifiers. Back-office teams must resolve medical-necessity, authorization, unit, and documentation denials before patterns consume the remaining episode.
Front-office
Referral, visit-limit, and authorization tracking - prevent noncovered therapy visits
Mid-office
Plan-of-care, progress-note, and timed-minute review - protect skilled therapy reimbursement
Back-office
Unit, modifier, and medical-necessity denial analysis - stop episode-wide payment failures
Protect authorized visits, timed units, and documented functional progress.
Track every authorized visit against the episode
Referral requirements, approved dates, and visit balances guide scheduling. Therapy does not continue unknowingly beyond payer authorization.
Align timed units with documented treatment minutes
Direct minutes, timed services, and total units reconcile before claim release. Payer audits find support instead of reconstructed therapy time.
Keep the plan of care clinically and financially active
Certification, goals, and progress reporting follow required milestones. Continued skilled therapy retains the documentation needed for payment.
Resolve therapy denials before they repeat across visits
Denial analysis connects units, modifiers, authorizations, and skilled-need evidence. Corrective action protects the remaining treatment episode from recurring loss.
Therapy billing expertise, visit-level intelligence, and episode governance connected.
Expertise-led
Therapy specialists connect clinical progression with visit-level billing rules.
- Coders calibrated on timed services, evaluation coding, and therapy modifiers
- Access specialists who track referrals, authorizations, and visit balances
- Denial analysts who test skilled need against plan and progress evidence
Technology-powered
RevAmp connects episode milestones with claim and payment exceptions.
- Rules surface expired authorizations, missing certifications, and unit mismatches
- Dashboards connect visits, documentation status, denials, aging, and cash
- Prioritized queues route therapy exceptions before another visit occurs
Operationally-governed
Episode performance follows evidence, ownership, and defined review cadence.
- Reviews track visit utilization, certification, timed units, modifiers, and denials
- Audits convert recurring minute and progress-note defects into education
- Operating reviews expose payer patterns, queue aging, actions, and outcomes
Our Vision
Open accountability: Taking responsibility without taking control.
Physical therapy leaders retain control of clinical standards, scheduling, and payer relationships. We bring specialists, RevAmp intelligence, and shared governance. Dashboards connect authorized visits, certification status, timed-unit accuracy, modifier use, progress reporting, denials, and aged accounts. Every exception carries a visit, therapist, payer rule, owner, and resolution deadline.

Authorized-visit utilization
Completed visits reconcile with approved dates and remaining balances
Plan certification timeliness
Plans and recertifications meet payer documentation milestones
Timed-unit accuracy
Direct minutes support billed units across timed therapy services
Therapy modifier accuracy
GP, KX, and CQ logic follows the visit record
Progress-note completion
Functional change and skilled need support continued treatment
Why Us
First-Pass Performance for certified plans, timed services, and authorized episodes.
Therapy defects compound across repeated visits. An untracked visit limit can create serial denials. Unsupported minutes can change unit allocation. Missing progress evidence can weaken continued care. First-Pass Performance connects scheduling, documentation, coding, and payer follow-up before the same defect spreads across the treatment episode.
Rework-Powered Cleanup Machine
Our First-Pass Performance
Visit-limit overrun
Authorization failures appear after another treatment visit occurs.
Visit balances and approved dates guide scheduling before service.
Plan certification gap
Missing signatures are chased after claims suspend or deny.
Certification status is monitored against the active treatment plan.
Timed-unit mismatch
Billing reconstructs minutes after documentation reaches coding.
Direct minutes and units reconcile before each therapy claim leaves.
Modifier logic defect
GP, KX, or CQ problems repeat across an episode.
Modifier conditions are tested against discipline, threshold, and PTA participation.
Progress-evidence failure
Continued care is defended only after medical-necessity denial.
Goals, functional change, and skilled need remain visible throughout treatment.
Revenue cycle thinking for leaders who need fewer surprises.
Explore Vee Healthtek perspectives on the forces reshaping revenue cycle performance, healthcare operations, technology adoption, and financial resilience.


Find where a therapy episode stops supporting payment.
Schedule a 30-minute working session with our therapy revenue cycle lead. Bring one pressure point: visit-limit tracking, plan certification, timed units, modifier use, progress notes, or recurring denials. We will map the defect across the episode, identify its financial effect, and define operating controls while your team retains clinical control.
Continue exploring expert perspectives, industry trends, and practical strategies for improving revenue cycle performance.
Explore Points Of ViewFrequently Asked Questions
How do you calculate timed units under the physical therapy 8-minute rule?

How do you track plan-of-care certification and recertification?
How do you prevent authorization and visit-limit denials?
When should GP, KX, and CQ modifiers appear on therapy claims?
How do you support medical necessity through therapy progress notes?
Which KPIs matter for physical therapy revenue cycle performance?
How does RevAmp prioritize therapy denials and A/R follow-up?